
The Implant Failed After I Delivered the Case. Here's What Happened Next.

This case is proof that the plan you start with is not always the plan you finish with.
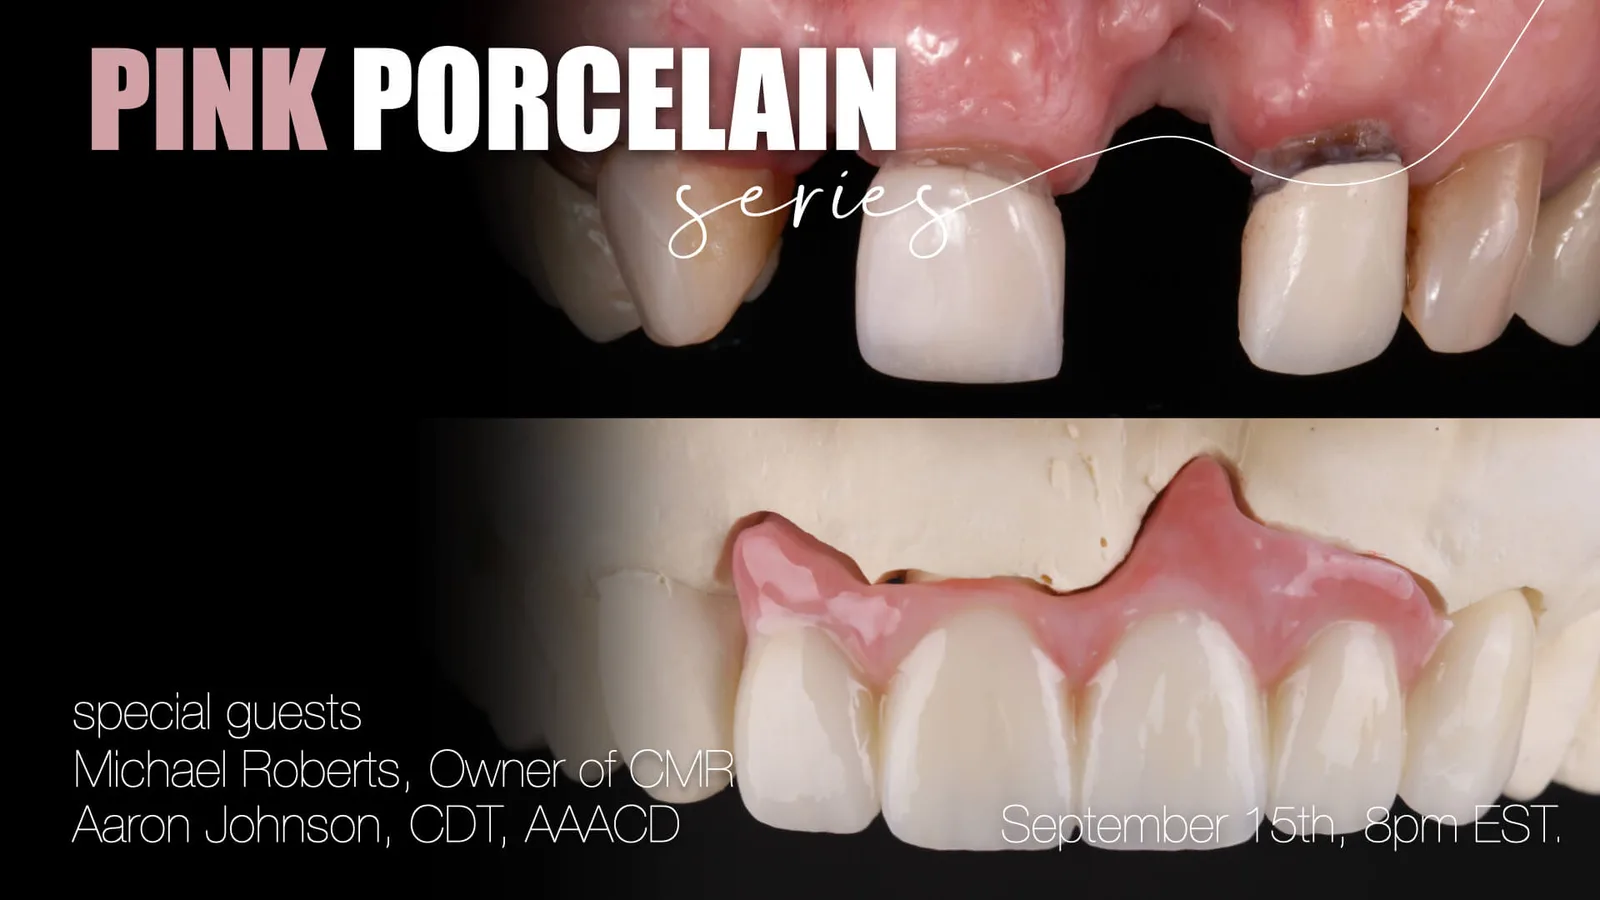
During a recent case discussion, part of a monthly series I host on Seay Within, I presented an anterior implant restoration that failed after delivery, and the three bridge designs it took to reach a result that integrated with the patient's tissue. The case involved a significant bone and soft tissue defect, but the larger lessons were about adapting when the plan changes more than once, and recognizing how much the pink design determines the final result.
My patient presented with bone loss, tissue loss, a failed bone graft, an existing bridge from #4 to #6, and a long dental history. The plan was an implant-supported bridge from #8 to #10, with pink porcelain to manage the tissue defect. For the restoration, I worked with Michael Roberts and Aaron Johnson of CMR, the ceramists I rely on for some of my most demanding cases.
When the First Bridge Failed After Delivery
The first bridge was esthetically strong at delivery. At the one-month post-operative visit, I noted heavy staining and began scaling. The implant at #7 was mobile enough to remove by hand.
The patient's surgeon happened to be in the office that day. The patient, who had said he would never return to a surgeon after everything he had been through, asked whether the implant could come out immediately. The surgeon removed it, and the treatment plan changed again.
Why the Second Bridge Would Not Seat
The second bridge spanned #7 to #11. It looked right, but at delivery it would not seat completely. The tissue in the #7 area continued to blanch even after I used electrosurgery to remove every interference I could find. The restoration looked correct, but the fit indicated a design problem. I called Michael to work through it.
Extending the Pink to Create a Uniform Gingival Line
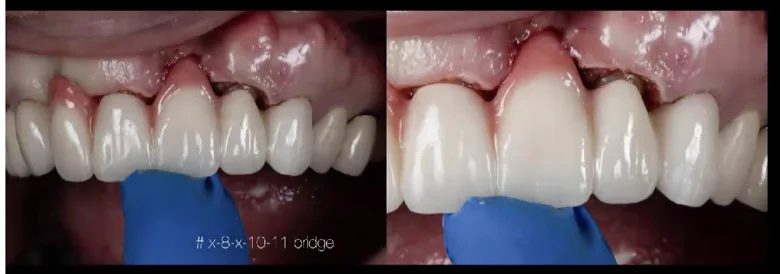
Michael proposed a different approach to the pink. He suggested shortening the clinical crown length of the centrals and laterals and extending the pink porcelain further cervically. This would create one continuous gingival band across the full bridge, rather than two separate pink sections meeting in the middle.
The redesign accomplished three things at once:
- It resolved the seating problem by releasing the design from the defect emergence profile at #8.
- It allowed a midline shift, because the restoration was no longer constrained by the former implant position.
- It created a papilla between the lateral incisor and canine that the previous design did not have.
Side by side, the difference is immediately visible. The second bridge reads as a restoration placed into a defect. The third reads as tissue that grew there.
How Pink Shade Changes Perceived Tooth Proportions
I use a pink composite in light, medium, and dark. Medium is the right choice about 80% of the time, but my supply had dried out when I made the first provisional, so I used light. Still out of medium for the second provisional, I used dark. Compared directly, the darker shade made the tissue zone more prominent, while the lighter shade allowed it to recede. With identical white designs, the teeth appeared proportionally different.
We select white shades with precision, using photographs, cross-polarization, and shade tabs. Pink deserves the same rigor. On cases like this, pink shade selection with your ceramist is part of the design.
Where Zirconia Gets Its Anatomy and Internal Color
Much of what makes a restoration like this succeed happens at the bench, before sintering. Zirconia is milled approximately 30% larger than its final sintered size. In this soft, carvable pre-sintered stage, the ceramist refines line angles, gingival contours, and surface texture by hand. Digital design establishes the architecture. Hand finishing brings it to life.
Internal characterization is applied to the porous zirconia at this stage as well. Pink tints, incisal gradients, and opacity adjustments are locked inside the material, so they read as depth rather than surface color. After an 8-hour sinter at 1600°C, characterization that looked faint going in reads clearly through the final restoration.
The pink layering combines liquid ceramics with powdered porcelain, which adds depth and texture that liquid ceramics cannot achieve alone. That is the difference between pink that looks applied and pink that looks like tissue.
Tissue Response Two Weeks After Final Delivery
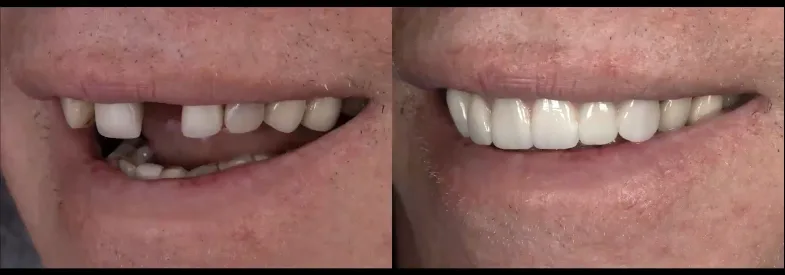
At the two-week follow-up, the tissue had adapted well. What appeared to be a marginal gap on delivery day was tissue recovering from cauterization and seating, and it had filled in completely. The patient was genuinely pleased, in the way someone is when a problem he has carried for years is finally resolved.
Some failures turn out to be productive ones. This case taught me more than any uneventful delivery could have.
Inside the Full 60-Minute Case Discussion:
- How shortening clinical crown length and extending the pink into a uniform gingival band resolved the seating issue, enabled a midline shift, and created a papilla between the lateral and canine
- Pink composite shade selection for provisionals, and how light, medium, and dark shades alter apparent tooth proportions even when the white design is identical
- Adding pink composite to a bisacryl provisional without overbulking: scribing the cervical line, reducing 1 to 2 mm of the facial surface in the pink zone, and layering to follow the existing anatomy
- Cementation under pink porcelain: why retraction cord is contraindicated, and how PTFE tape wrapped around the tooth neck and packed into the sulcus allows clean gel-state cleanup
- Ridge lap versus seating on the ridge: why pink porcelain begins at tooth structure rather than overlapping soft tissue, allowing self-cleansing access while creating the illusion of natural tissue emergence
- When to modify an existing implant crown for provisional use rather than fabricate a new custom abutment
Join Seay Within's Case Continuum for access to 40+ short-form clinical tips and over 30 case discussions, plus monthly live sessions.
About the Author

Dr. Amanda Seay
Charleston, South Carolina